

OCD affects about 1% to 3% of people in Canada, with a lifetime prevalence of 2.3%, and it isn't just about cleanliness or being “particular.” It's a real, treatable mental health condition involving intrusive thoughts and repetitive behaviours, and ERP therapy helps many people improve.
If you're reading this because you're worried about yourself, your child, or someone you love, you may already know how confusing OCD can feel. Many people recognise that something is wrong, but they can't easily explain it. They may say, “I know this doesn't make sense, but I still feel like I have to do it.” That gap between logic and feeling is one of the hardest parts of OCD.
'Obsessive-Compulsive Disorder is a manageable medical condition characterized by a distressing cycle of intrusive thoughts (obsessions) and repetitive behaviours (compulsions); it is not a personality quirk or a character flaw.'
OCD explained, simply, means understanding that the problem isn't the presence of strange thoughts. It's the painful cycle of doubt, alarm, and certainty-seeking that keeps getting reinforced.
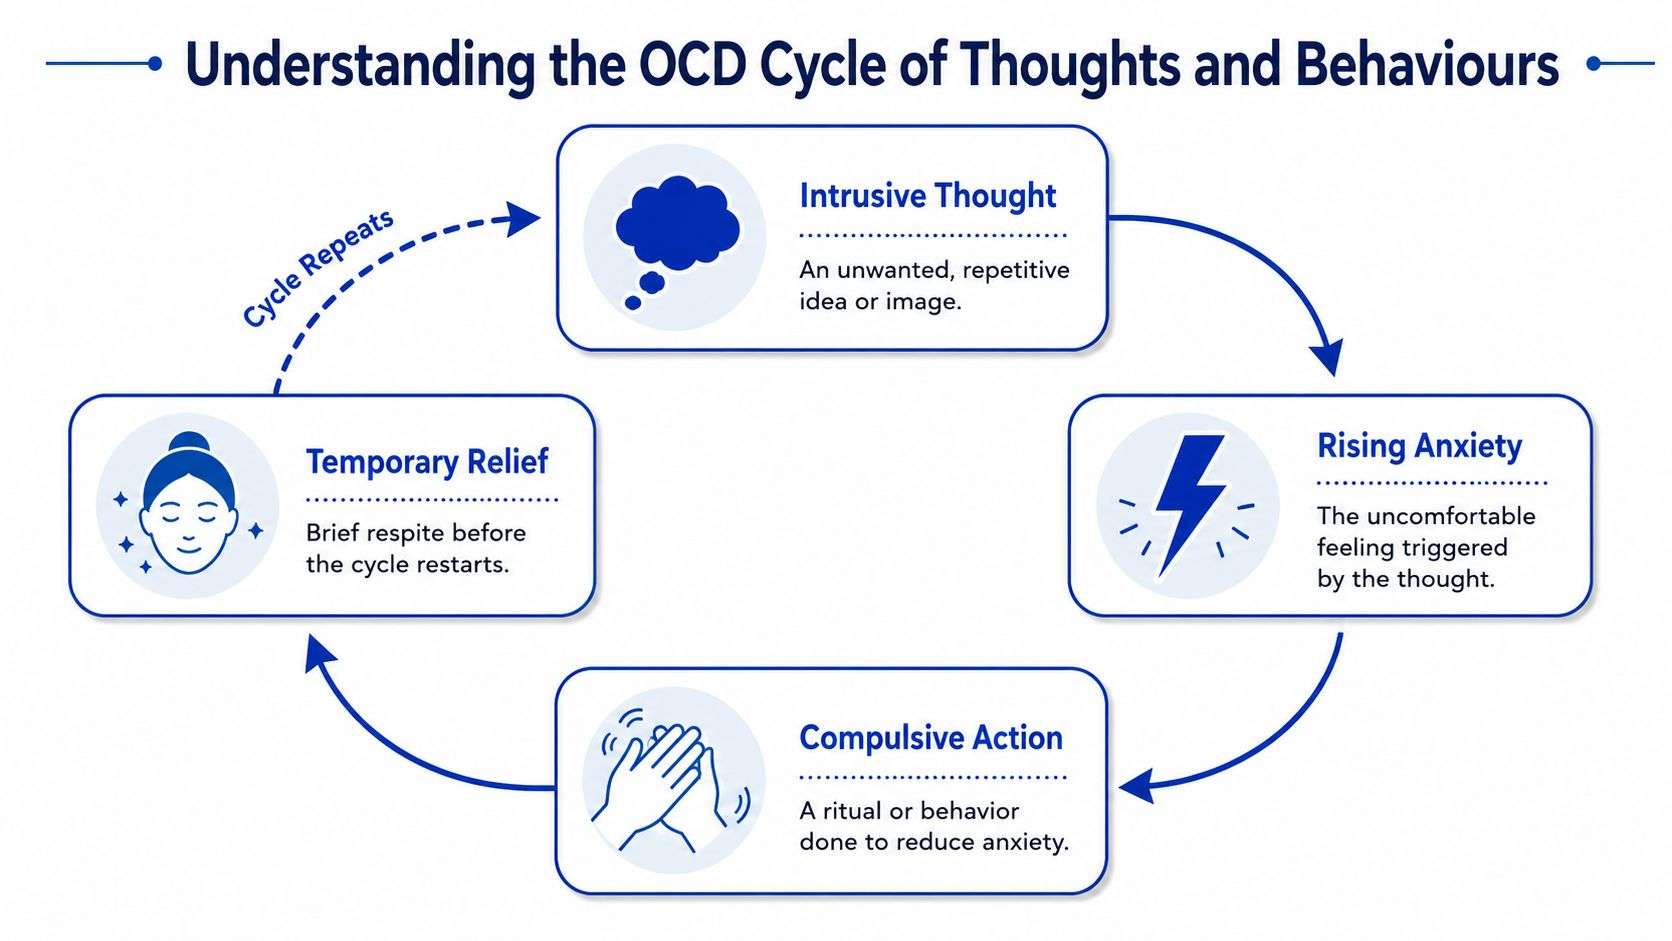
Understanding the OCD Cycle of Thoughts and Behaviours
A person has a sudden thought: What if I left the stove on? Another person has an image they never wanted: What if I hurt someone? A child feels a powerful sense that something is “not right” unless they tap the desk a certain number of times.
These experiences can feel very different on the surface, but the pattern underneath is often the same.
What obsessions and compulsions actually mean
Obsessions are unwanted, intrusive thoughts, images, or urges that trigger distress. They often feel sticky, loud, and hard to dismiss. The person usually doesn't want them, agree with them, or feel represented by them.
Compulsions are the actions someone does to reduce that distress. Sometimes they're visible, like washing, checking, repeating, arranging, or seeking reassurance. Sometimes they happen internally, like reviewing memories, repeating phrases in your mind, or trying to “cancel out” a thought.
For a clinical diagnosis of OCD in Canada, symptoms must be time-consuming, typically occupying more than one hour per day, or cause significant impairment in social, occupational, or other important areas of functioning. That's what separates OCD from the occasional odd or upsetting thought commonly experienced.
Why the cycle keeps going
A simple way to think about OCD is this: the brain's alarm system becomes too sensitive, like a smoke alarm that blares because of burnt toast instead of a house fire.
The cycle often looks like this:
- Intrusive thought appears: “What if I contaminated my hands?”
- Anxiety rises: The body reacts as if danger is present now.
- Compulsion happens: Washing, checking, confessing, avoiding, praying, mentally reviewing.
- Relief shows up briefly: The nervous system settles for a moment.
- The brain learns the wrong lesson: “That ritual kept me safe.”
That last part matters. The compulsion works in the short term, so the brain keeps asking for it again. That's why OCD can feel relentless even when the person knows, logically, that the fear may not fit the facts.
Where people often get confused
Many readers assume the obsession is the main problem. Often, it isn't. The trap is the response pattern that follows.
Practical rule: If a behaviour gives quick relief from OCD fear but makes the fear stronger later, it's probably feeding the cycle.
Stress, poor sleep, and exhaustion can make the cycle louder. For some readers, broader support around nervous system regulation also helps alongside OCD treatment. If stress is affecting rest, this guide on how to improve sleep naturally may be a useful companion resource.
What OCD Is Not Debunking Common and Harmful Myths
OCD gets misunderstood in everyday conversation. That misunderstanding can leave people feeling ashamed, dismissed, or afraid to ask for help. A clearer understanding makes a real difference.
In Canada, OCD is estimated to affect approximately 2.5% of the general population, and women are often diagnosed at a ratio of roughly 1.6 to 1 compared to men. This isn't a rare personality style. It's a recognised mental health condition.
Myth and reality
| Myth | Reality |
|---|---|
| OCD is just about being neat or organised. | Some people with OCD do struggle with contamination, order, or symmetry, but many do not. OCD can centre on harm, morality, relationships, religion, sexuality, health, or a vague feeling that something is off. |
| Everyone is a little OCD. | Most people have occasional intrusive thoughts. OCD involves a distressing cycle that becomes time-consuming or significantly impairing. |
| People with OCD should just stop overthinking. | OCD isn't solved by willpower. The condition involves brain-based difficulty with doubt, alarm, and inhibition. |
| OCD means someone secretly wants the thought to be true. | Intrusive thoughts in OCD are usually ego-dystonic, meaning they clash with the person's values and identity. That clash is often why they feel so upsetting. |
What “not just a quirk” really means
When people say, “I'm so OCD,” they usually mean they like things tidy or done a certain way. That casual use misses the distress at the centre of the disorder.
A person with OCD may spend hours trying to get certainty they can never fully achieve. They may ask loved ones the same question repeatedly, avoid normal activities, or feel trapped by rituals that make little sense to anyone else, including them.
“Everyone gets strange thoughts sometimes. OCD is what happens when the brain treats those thoughts like emergencies.”
The shame problem
One of the most painful myths is that OCD reflects weak character, hidden desire, or a lack of self-control. It doesn't.
OCD is not a moral failure. It's not a sign that someone is careless, dangerous, manipulative, or “dramatic.” People with OCD are often working strenuously just to get through ordinary parts of the day that other people barely notice.
That's why accurate language matters. It replaces judgment with understanding, and it makes it easier for families to respond with support instead of criticism.
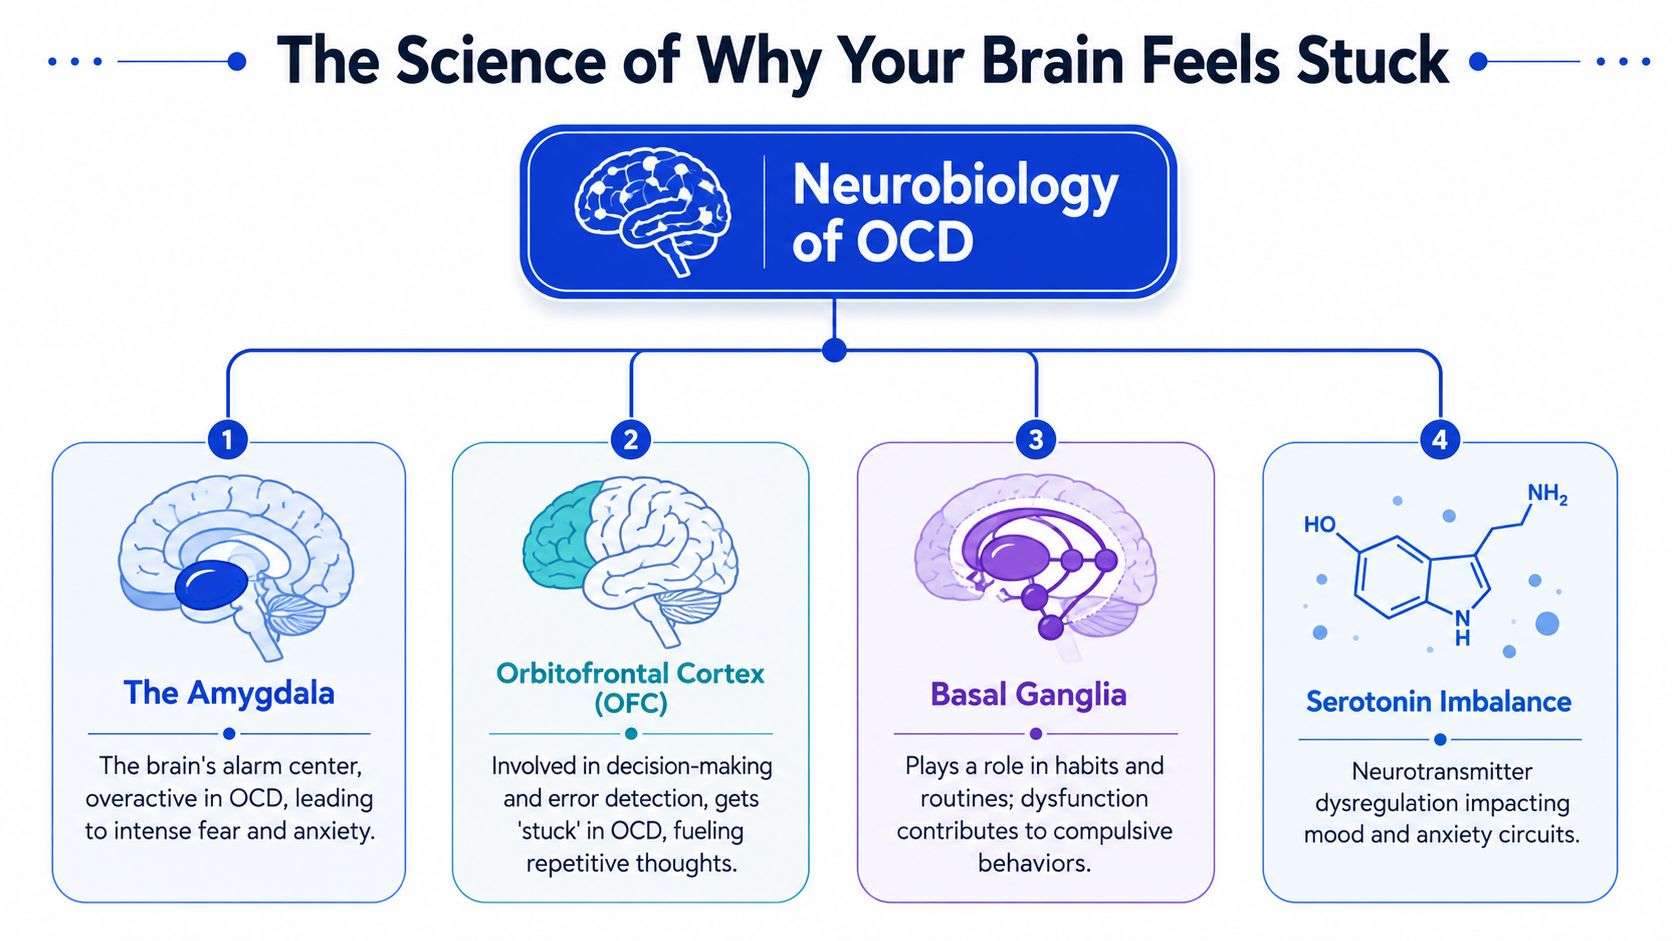
The Science of Why Your Brain Feels Stuck
Many people with OCD say some version of the same thing: “I know it sounds irrational, but it feels completely real.” That feeling has a biological basis.
Researchers understand OCD as a disorder involving dysfunctional neural networks in the cortico-striato-thalamo-cortical (CSTC) loop. Rather than one broken spot in the brain, it's better understood as a communication problem in circuits involved in error detection, inhibition, habit, and uncertainty.
The stuck gear problem
A plain-language way to describe OCD is brain lock. The brain's internal “something is wrong” signal turns on too strongly, and the system that should help you shift away from that signal doesn't work efficiently enough.
Verified neurobiological descriptions of OCD note a “hyper-activation” of error-monitoring systems and an “inefficient linkage” between the brain's error-recognition system and its inhibitory control system. In everyday terms, the brain over-detects possible error and under-stops the urge to fix it.
That can create the haunting sense of:
- Persistent doubt: “But what if?”
- Inflated urgency: “I need to solve this now.”
- False incompleteness: “It still doesn't feel right.”
- Compulsive correction: “Maybe one more check will settle it.”
Why certainty-seeking backfires
The brain likes certainty. OCD becomes especially painful because it targets uncertainty itself.
A person checks the lock to feel sure. Then they doubt their memory. Then they check again, not because they're careless, but because the checking itself weakens trust in their own internal signal. The ritual becomes a substitute for confidence, and that substitute never lasts.
The more OCD asks for certainty, the less certainty a person tends to feel.
This is one reason reassurance often helps only briefly. Even kind, loving reassurance can become part of the stuck pattern if it serves the same role as a ritual.
This is medical, not a weakness
The science matters because it changes the story people tell themselves. If your brain keeps sending a false alarm, that doesn't mean you're failing. It means your system is getting caught in a loop.
That's also why targeted therapy can help. Good OCD treatment isn't random talking about stress. It directly works with the brain systems involved in alarm, inhibition, and uncertainty.
How Evidence-Based Therapy Retrains Your Brain
The most effective treatment for OCD isn't trying to argue every thought away. It's learning a new response when the thought appears.
Exposure and Response Prevention (ERP) is a specialised form of Cognitive Behavioural Therapy (CBT) and is recognised in Canadian clinical guidance as the gold-standard, first-line treatment for OCD. Studies cited in those guidelines show that up to 70 to 80% of individuals achieve significant symptom reduction when adhering to a structured ERP protocol.

What ERP looks like in real life
ERP has two parts.
Exposure means gradually facing the thought, image, object, situation, or feeling that triggers OCD.
Response prevention means resisting the ritual that usually follows.
If someone fears contamination, an exposure might involve touching a doorknob and waiting before washing. If someone fears making a terrible mistake, it might involve sending an email without re-reading it repeatedly. If someone has primarily mental rituals, the work may focus on allowing the thought to be present without analysing, neutralising, or seeking reassurance.
Why this works in the brain
ERP helps retrain the brain by repeatedly allowing the alarm to rise and then fall without the compulsion. Over time, the brain learns something new: “This feeling is uncomfortable, but it isn't dangerous, and I don't need a ritual to survive it.”
That's why ERP is often compared to learning to enter cold water slowly or building a muscle through repeated practice. The goal isn't to force someone into panic. The goal is careful, supported practice that strengthens tolerance for uncertainty.
Research descriptions of OCD treatment note that ERP targets the same dysfunctional circuitry involved in the disorder. In practical terms, therapy isn't only changing habits. It's helping the brain form new patterns.
What therapy is not trying to do
ERP does not aim to erase intrusive thoughts completely. It is common for individuals, with or without OCD, to experience unwanted thoughts at times.
The therapeutic target is different:
- Less fear of the thought
- Less urgency to get certainty
- Less dependence on rituals
- More freedom to act according to values
Recovery often begins when a person stops asking, “How do I make this thought go away?” and starts asking, “How do I stop obeying it?”
Some people also use medication as part of treatment. That decision is personal and best discussed with a qualified medical provider. For many people, the strongest progress comes from a plan that is evidence-based, specific to OCD, and paced in a way that feels manageable.
What to Expect from OCD Counselling
Starting counselling for OCD can feel vulnerable, especially if the thoughts are embarrassing, violent, sexual, blasphemous, or otherwise taboo. Many people delay getting help because they fear being misunderstood. A skilled therapist knows that intrusive thoughts are a symptom, not a confession.
The first stage of counselling usually focuses on understanding your pattern clearly. That includes what the obsessions sound like, what compulsions you do, what situations you avoid, and how OCD pulls others into the cycle.

Early sessions often feel like this
A therapist may ask questions such as:
- What happens first: Is it a thought, a body sensation, an image, or a feeling of wrongness?
- What do you do next: Checking, asking, avoiding, confessing, researching, reviewing?
- What relief do you get: How long does it last before doubt comes back?
- What is OCD costing you: Time, sleep, relationships, school, work, energy?
That mapping matters because treatment works best when it fits the exact cycle, not a generic idea of anxiety.
Building a fear ladder together
Many therapists use an ERP hierarchy, sometimes called a fear ladder. This is a list of triggers ranked from easier to harder. You don't start at the most overwhelming item. You build confidence by practising manageable steps first.
A fear ladder might include:
- Mild step: Read a triggering word and resist reassurance.
- Moderate step: Touch an object once and delay a ritual.
- Harder step: Enter a feared situation and leave without checking.
The process should feel collaborative. Ethical OCD therapy doesn't force, shame, or surprise clients with exposures they haven't agreed to.
Good OCD counselling is active, respectful, and paced. You should feel challenged, but you should also feel supported.
If you'd like to understand [object Object], it can help to read more about our approach to counselling, including how evidence-informed care is individualized to different needs and comfort levels.
Supporting Children and Families Through OCD
When OCD affects a child or teen, the whole family often feels it. Parents may find themselves answering the same reassurance question over and over, helping with rituals, changing routines, or avoiding triggers to keep the peace. Those responses usually come from love.
They can also accidentally strengthen OCD.
When helping starts to feed the cycle
This pattern is often called accommodation. A caregiver might check homework repeatedly because the child can't tolerate uncertainty, sleep beside them because bedtime rituals have expanded, or avoid certain words because they trigger panic.
Accommodation makes sense in the moment. It lowers distress quickly. But over time, it can teach the child that they really can't cope unless the family helps complete the ritual.
Common family traps include:
- Reassurance loops: Repeatedly answering, “Are you sure?”
- Participation in rituals: Checking, arranging, washing, repeating.
- Avoidance patterns: Removing every trigger from daily life.
- Conflict cycles: Frustration rises, and everyone feels blamed.
What support can look like instead
Children need compassion first. They also need adults who can separate the child from the OCD.
That may sound like:
- “I can see OCD is being loud right now.”
- “I won't help the ritual, but I will help you get through the feeling.”
- “You're safe, and we can practise being brave together.”
For younger children, therapy may use age-appropriate tools such as drawing, stories, games, or simple visual scales to teach exposure principles. Teens often benefit from a more direct explanation of how OCD works and why rituals keep it going.
Family involvement can be powerful when it helps everyone respond more consistently, reduce accommodation, and reinforce courage rather than certainty-seeking.
Frequently Asked Questions About OCD
Can you have OCD without obvious compulsions
Yes. Some people have what's often called Pure O, meaning their symptoms are dominated by intrusive thoughts and less visible compulsions. The compulsions still exist, but they may happen mentally through rumination, checking memories, repeating phrases, praying, or seeking internal certainty.
Verified data notes that approximately 25 to 30% of clinically diagnosed OCD cases present primarily as “Pure O,” yet a 2025 review of Canadian OCD clinical guidelines found that only 40% of public health informational materials explicitly address this subtype's treatment parity. That gap can leave people wrongly believing that standard OCD therapy won't help them.
The important point is this: ERP can be effective for Pure O too.
Can OCD be cured
People use the word “cure” in different ways. A more helpful frame is that OCD is manageable, and many people improve significantly with proper treatment. Some people reach a point where symptoms are mild and no longer run their lives. Others continue to have occasional flare-ups but know how to respond without falling fully back into the cycle.
Progress usually means greater freedom, not perfect mental silence.
How do I support a loved one without making OCD worse
Support works best when it is warm but boundaried. Try to validate the distress without joining the ritual.
A helpful pattern is:
- Acknowledge the feeling: “I can see this is hard.”
- Name the disorder gently: “This sounds like OCD asking for certainty.”
- Avoid ritual participation: Don't repeatedly reassure, check, or help avoid.
- Encourage treatment skills: Support the person in using what they're practising in therapy.
For families looking for broader emotional skill-building, age-appropriate evidence-informed resilience activities can complement, but not replace, OCD-specific treatment.
What if the intrusive thoughts are violent, sexual, or disturbing
That's one of the most frightening parts of OCD, and also one of the most misunderstood. Intrusive thoughts in OCD often target exactly what the person cares about most. The presence of a thought does not equal intent, desire, or danger.
This is one reason people feel enormous shame and keep symptoms secret. A therapist trained in OCD should understand that taboo obsessions are a recognised presentation of the disorder.
When should someone seek help
If obsessions or compulsions are taking up substantial time, causing distress, affecting relationships, interfering with work or school, or shrinking a person's life, it's time to seek help. Earlier treatment often means less time spent trapped in the cycle and more time learning how to respond effectively.
If you're looking for a place to learn more about OCD support, Interactive Counselling offers information about evidence-informed counselling for individuals, children, youth, couples, and families. Reaching out for clarity doesn't mean something is wrong with you. It means you're taking your distress seriously and looking for a steadier way forward.
Clinically Reviewed By
Amy Mosset, MCP, RCC-S
Amy Mosset is a Master Practitioner in Clinical Counselling, Clinical Supervisor, and the owner of Interactive Counselling. She provides trauma-informed, evidence-based care and clinical supervision to registered therapists, with a focus on ethical practice, client safety, and high-quality therapeutic outcomes.


