Trauma counselling is a practical part of doing this job safely. In Alberta, first responders experience PTSD at about twice the rate of the average population, and in Edmonton approved psychological injury claims within the Edmonton Police Service rose from 36 to 145, which had quadrupled since 2019. For more information, see our trauma counselling.
"First responder trauma counselling for RCMP and EMS in Northern Alberta means finding confidential, trauma-informed support that fits the realities of cumulative stress, small-community privacy concerns, and the demands of staying functional on the job."
There's a familiar stretch of time after a hard call when everything goes quiet. The road is long, the radio finally stops, and your body is still running as if the call hasn't ended. You get home, but you don't fully arrive. You eat because you should. You try to sleep. You snap at someone you care about, or you say nothing at all.
For many RCMP members and EMS professionals in Northern Alberta, that isn't a dramatic crisis moment. It's just another shift ending badly. It's also one of the clearest signs that your system may need support, not because you're failing, but because the work keeps asking your nervous system to absorb more than any person is meant to carry alone.

A Quiet Acknowledgement for a Loud Job
Alberta has formally recognized what first responders already know from experience. The province says first responders are regularly exposed to traumatic events and chronic occupational stress that create disproportionately high rates of mental health crises, and it notes that first responders experience PTSD at about twice the rate of the average population through its first responders' mental health grants information.
That matters because it moves this out of the realm of personal weakness. This is an occupational hazard. The same way agencies talk about scene safety, fatigue, or operational readiness, mental health belongs in the same conversation.
If you work in a smaller detachment area or cover long rural transport routes, this can feel even harder to admit. People know each other. People notice things. Privacy can feel thin. That's one reason conversations about Safety Space on safety culture are useful. A strong safety culture includes psychological safety, not just physical risk management.
Practical rule: If the job is affecting your sleep, temper, relationships, concentration, or sense of who you are, that's enough reason to talk to someone.
A lot of first responders wait because they think counselling only makes sense after one catastrophic event. In practice, many people seek help because of the steady build-up. The bad fatality. The child call. The suicide. The domestic. The shift shortage. The paperwork after the call. The call that should have ended differently. The call that looked routine and stayed with you anyway.
What support can look like
Good support is rarely dramatic. It often starts with simple, solid work:
- Getting your sleep more stable so your body isn't living in constant activation
- Reducing the spillover home so you're less irritable, shut down, or on edge
- Making sense of repeated exposure instead of trying to dismiss it
- Creating a private plan that protects your dignity and your career concerns
If you want a clearer sense of what trauma-focused support can involve, [object Object] is one neutral starting point for learning about counselling options.
Clinically Reviewed By
Amy Mosset, MCP, RCC-S
Amy Mosset is a Master Practitioner in Clinical Counselling, Clinical Supervisor, and the owner of Interactive Counselling. She provides trauma-informed, evidence-based care and clinical supervision to registered therapists, with a focus on ethical practice, client safety, and high-quality therapeutic outcomes.
Understanding When It Is More Than Just a Bad Day
A bad day usually passes. Cumulative trauma lingers.
It doesn't always show up as obvious flashbacks or a clear moment where you think, “Something is wrong.” More often, it creeps in through habits, reactions, and changes that become easy to normalize because everyone around you also works under pressure.
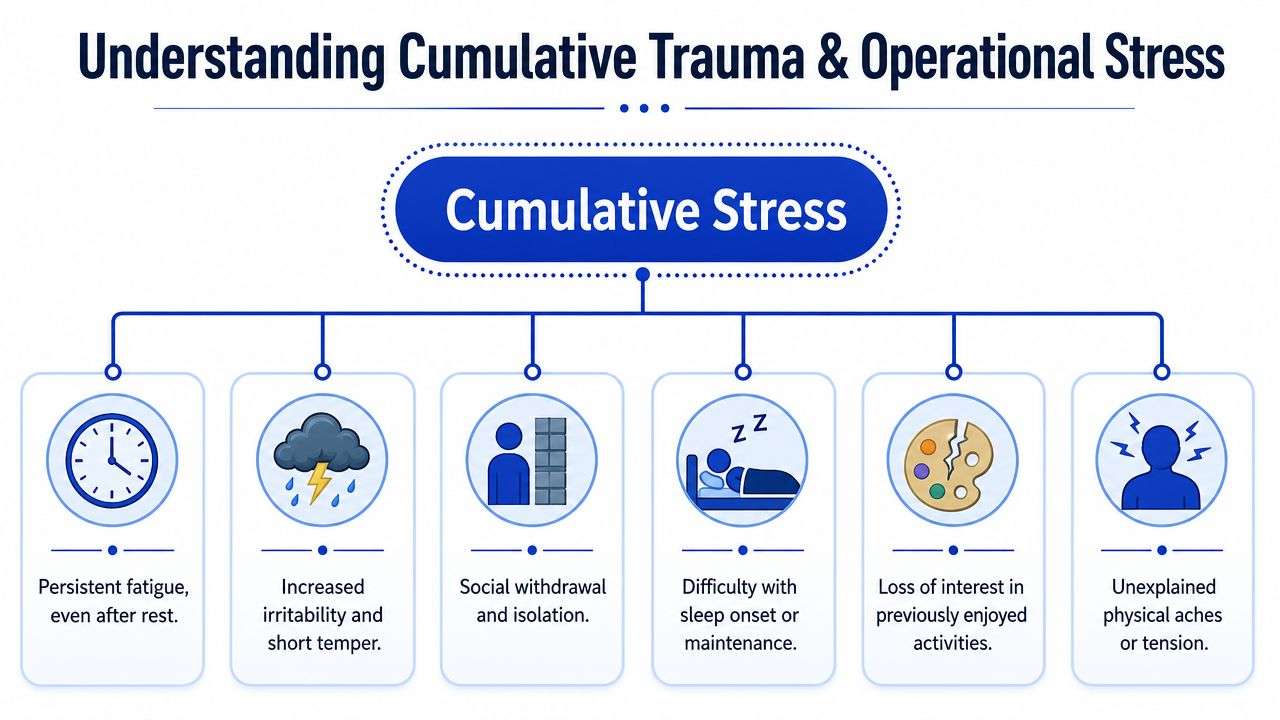
Common signs that deserve attention
You may notice:
- Sleep changing first. You're tired but can't settle, or you wake as if you're still on shift.
- A shorter fuse. Small frustrations land harder than they used to.
- Emotional numbing. You can perform at work, but you feel flat at home.
- Pulling back from people. It seems easier not to talk, explain, or connect.
- A harder worldview. Cynicism starts to feel like protection.
- Physical tension. Headaches, jaw clenching, stomach issues, and constant muscle tightness often travel with stress injuries.
These signs don't automatically mean PTSD. They do suggest your nervous system may be overloaded.
Why this is not “just in your head”
In Edmonton, workers' compensation data showed approved claims for psychological injuries within the Edmonton Police Service had quadrupled since 2019, rising from 36 to 145, and the same reporting described hundreds of first responders needing to step away from duty and spend months off work on average in some cases, which shows how strongly trauma exposure can affect staffing and recovery in Alberta settings, as reported in this Edmonton regional benchmark on psychological injury claims.
That kind of benchmark matters because it tells the truth about scale. This is not rare. It's not limited to one personality type. It's not a sign that someone “couldn't handle it.” It's what can happen in jobs built around repeated exposure to distress, danger, loss, and moral pressure.
Many RCMP and EMS members aren't asking, “Do I have one big trauma?” They're asking, “Why can't I reset anymore?”
Single-incident trauma and cumulative stress are not the same
A single critical incident can leave a sharp, obvious mark. Cumulative operational stress tends to wear people down more subtly. You may keep functioning for a long time while your off-duty life starts narrowing. Your patience drops. Your sleep gets lighter. Your body stays prepared for impact.
A useful self-check is this: are you recovering between shifts, or only surviving them?
If recovery isn't happening, support makes sense now. Not later, when things become harder to hide and harder to treat.
Your Map to Finding the Right Support
Most first responders do best with layered care, not a single all-or-nothing solution. Guidance from SAMHSA recommends a multi-layered model that includes peer support for early identification, leadership communication, routine welfare checks, assignment rotation, peer monitoring, and rapid referral to psychotherapy. The same source summary also notes a later critical review finding that peer programs can reduce common barriers to accessing care, which you can read in this SAMHSA guidance for first responder behavioural health.
That's important because the right first step depends on what you need today. Some people need a private conversation with a peer. Some need structured therapy. Some need both.
Three common entry points
| Pathway | What it helps with | Limits to keep in mind |
|---|---|---|
| Peer support | Early check-ins, stigma reduction, talking to someone who understands the culture | Not a replacement for therapy when symptoms are persistent, escalating, or affecting function |
| Employer or union-linked supports | Access to short-term support, referrals, benefit navigation | Some first responders worry about privacy, fit, or whether the provider understands public safety work |
| Independent counselling | Greater control over provider choice, pace, format, and privacy | You may need to do more of the setup yourself, including checking benefits or arranging scheduling |
What tends to work best
The strongest approach is often practical rather than ideological. Start where the barrier is lowest, then step up care if needed.
For example:
- If you don't trust therapy yet, a trained peer or buddy system may be the safest first contact.
- If you need fast symptom relief, counselling focused on sleep, anxiety, and regulation may be more useful than detailed trauma processing right away.
- If confidentiality is your main concern, independent counselling may feel easier to control.
- If your symptoms are affecting home and work, combine peer support with a therapist who understands trauma and occupational stress.
What usually doesn't work
A few patterns consistently create problems:
- Waiting for total collapse before reaching out
- Using one difficult call as the only benchmark, when the underlying issue is cumulative exposure
- Relying on informal venting alone without follow-up or structured care
- Assuming every counsellor understands first responder culture without asking
One option among others is Interactive Counselling, which offers in-person, phone, and secure virtual counselling in Canada. The format matters because many first responders need care that can fit shift work and privacy needs rather than a rigid office-only model.
Keeping Your Search for Help Private
For many RCMP and EMS professionals in Northern Alberta, privacy is the whole issue.
The hesitation often isn't about whether counselling could help. It's about whether seeking help will affect your reputation, your file, your team relationships, or the way people look at you after they know. In smaller communities, that concern is real. You may know the receptionist. Your supervisor may know the therapist's family. Your neighbour may work in the same building.

Why privacy matters so much in the North
Alberta paramedic resources point people toward confidential, off-site supports and crisis resources rather than only employer-linked care, and PSPNET-related guidance notes that first responders value completely private, self-guided support that can be accessed without telling colleagues or supervisors. For people in smaller Northern Alberta communities where specialist options may be limited, those realities make virtual care especially useful, as reflected in this Alberta paramedic mental health resource sheet.
That tells us something very practical. Privacy isn't a luxury issue. It's an access issue.
Ways to protect your confidentiality
If anonymity is your top priority, these steps often help:
- Use a personal device and personal email for first contact, not a work phone or work account.
- Ask about confidentiality directly before booking. A good therapist will explain it clearly and calmly.
- Choose virtual sessions if local visibility is a concern.
- Book at times that don't draw attention. Some people prefer days off. Others prefer before or after shifts.
- Look for off-site support rather than only using the most obvious local route.
Private access is often the difference between delaying care and actually beginning it.
What confidential counselling usually means
In counselling, your information is generally protected within professional and legal limits. A therapist should explain those limits plainly at the start, including situations involving immediate safety risk or other required exceptions. Most of the time, the first thing clients need is not a legal lecture. They need to hear, clearly, that therapy is not a casual information-sharing environment.
If you're worried, ask direct questions:
- Who sees my file?
- How is information stored?
- Will my employer be notified?
- Can I attend virtually from home or another private location?
- What name or contact method will you use for reminders?
These are reasonable questions. They do not make you difficult. They show good judgment.
Virtual care can be the most realistic entry point
For Northern Alberta first responders, virtual counselling often solves two problems at once. It expands access to clinicians with trauma experience, and it reduces the chance of being seen walking into a local office. It also fits the circumstances of shift work, weather, distance, and long transport routes more easily than a fixed in-person schedule.
For some people, that privacy is what finally makes first responder trauma counselling for RCMP and EMS in Northern Alberta feel possible.
How to Get Started with Funding and Access
Finances stop many people before they start, especially when energy is already low. The good news is that you don't need to solve everything at once. You only need a clear first pass through your options.
Start with the quietest route
Begin by checking the supports that don't require public disclosure.
That may include:
- Extended health benefits through employment or a family plan
- Union or association resources if they apply to your role
- Employee assistance options for short-term support or referral
- Provincial programs related to first responder mental health
Alberta's continued funding of first responders' mental health grants signals that the province treats this as a workforce issue, not a fringe benefit. If you're also trying to understand how workplace support programs are generally structured, this overview of essential EAP benefits for modern workplaces can help you know what kinds of features to look for.
Questions worth asking before you book
When you contact a benefits provider or review a plan, keep it simple:
- Does my plan include counselling with a registered professional?
- Do I need a doctor's referral?
- Can I choose my own provider?
- Are virtual sessions covered?
- Is there a session limit or approval process?
- How are claims submitted, and what information appears on statements?
Those last questions matter if privacy in your household or workplace is a concern.
Keep the process manageable
If paperwork feels overwhelming, use a two-step approach.
First, identify one usable path. Second, book one first appointment. Don't wait until you've researched every program, every funding stream, and every therapist. That kind of over-preparation often becomes avoidance, especially when you're already exhausted.
The goal is not to build the perfect care plan on day one. The goal is to open one safe door.
What Happens in a Trauma Counselling Session
Many first responders are less afraid of the work than they are of the unknown. They don't want to walk into a session and get pushed into talking about the worst call of their career before trust exists.
That isn't what good trauma-informed care looks like.
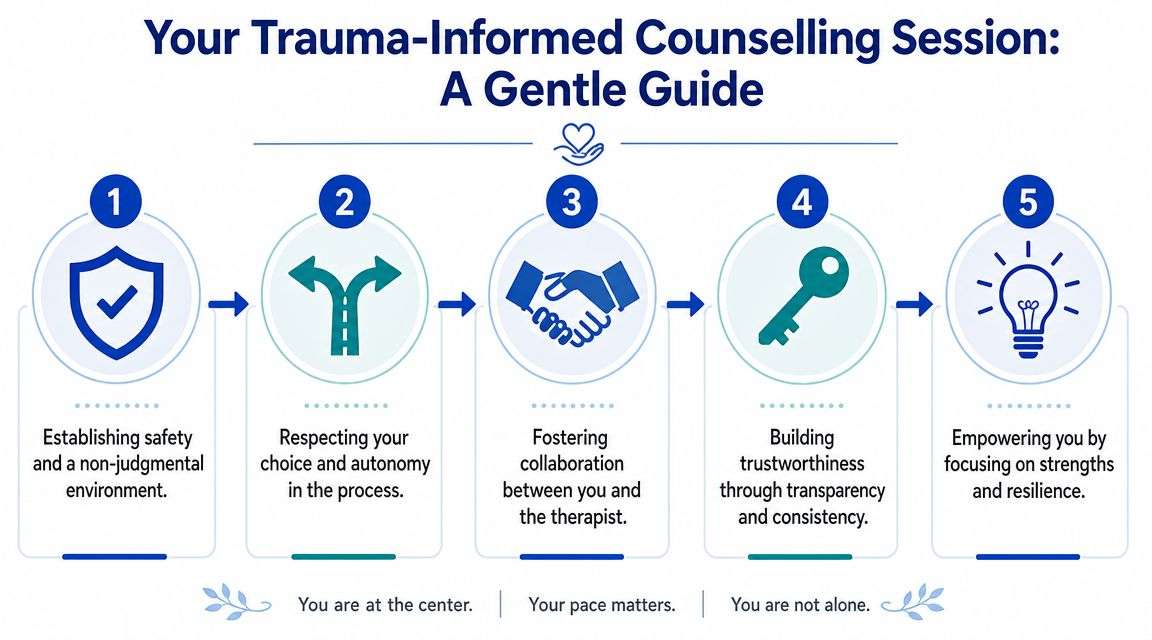
The first session is usually practical
For many Northern Alberta first responders, the issue is cumulative operational stress rather than one clearly defined event. Alberta first responder resources support a stepped-care model where support often starts with stabilization, such as improving sleep and stress, before moving into deeper trauma work.
In plain terms, the first session often focuses on questions like:
- What's been hardest lately?
- What happens in your body when you try to rest?
- What are you noticing at home, on shift, or between calls?
- What do you want help with first?
That last question matters. Your goals shape the work.
You stay in control of the pace
Trauma-informed counselling is built around safety, collaboration, choice, and transparency. A therapist should not force disclosure, rush trust, or assume that recounting every detail is the fastest path to healing.
Early work often includes:
- Stabilization skills for sleep, hypervigilance, and anxiety
- Nervous system regulation so your body can come down from constant activation
- Functional goals such as getting through shifts with less spillover at home
- A plan for deeper work later, if and when that feels appropriate
Therapy is not only about retelling the story
Some first responders need trauma processing. Some need help with moral injury, irritability, insomnia, or emotional shutdown before they are ready to go near a memory in detail. Some never need extensive retelling to make meaningful progress.
A good session should leave you feeling more oriented and less alone, not exposed and destabilized.
If a therapist is trauma-informed, they understand that effective first responder trauma counselling for RCMP and EMS in Northern Alberta often begins with restoring basic steadiness. Sleep. Breathing room. Less reactivity. More choice. That foundation is not a delay. It is treatment.
Frequently Asked Questions About First Responder Counselling
What if I'm not in a full mental health crisis, but I know something is off
You do not need to wait for a breakdown, medical leave, or a formal diagnosis to seek help. In first responder work, earlier support is often more practical because it can address the signs that appear before things become harder to manage. That might mean poor sleep, detachment, irritability, intrusive memories, dread before shift, or trouble coming down after calls.
A lot of people minimize these signs because they're still functioning. They're showing up, completing reports, making decisions, and getting through the week. But “still functioning” isn't the same as doing well. If the job is changing how you live, connect, rest, or cope, that's enough reason to talk to someone. Counselling can start with stabilization and practical symptom management. It doesn't have to begin with a crisis.
How do I talk to my partner or family about getting help
Keep it simple and specific. You do not need to deliver a polished explanation of trauma. You can say that the job has been catching up with you, and you want support before it affects things more. If talking in emotional language feels unnatural, describe what they may already have noticed: trouble sleeping, being more shut down, being more irritable, or having less patience and energy.
You can also tell them what you need from them. Maybe that's privacy. Maybe that's help protecting appointment time. Maybe it's just not having to explain every detail of a call. Family members often feel relieved when there is a plan, even a small one. The conversation usually goes better when you frame counselling as maintenance and support, not as a sign that everything is falling apart.
Is therapy always about talking through traumatic calls in detail
No. That's one of the most common misconceptions.
Trauma counselling can include processing difficult events, but that is not always the first step and it is not always the central task. For many first responders, the immediate need is better sleep, less hypervigilance, improved emotional regulation, and a way to stay functional while still working. A trauma-informed therapist will usually pace the work carefully and collaborate with you about what feels useful and what feels too much.
If you're dealing with cumulative stress, the focus may begin with patterns rather than one scene. You might work on how your body stays activated, how your mood shifts after repeated exposure, or how work stress follows you home. Good therapy should be structured enough to help, but flexible enough to respect your limits.
What should I do if I need help right now
If you are in immediate danger, thinking you may act on suicidal thoughts, or you cannot stay safe, contact emergency services right away or go to the nearest emergency department. If immediate crisis support feels more reachable than a full counselling appointment, use a confidential crisis line or urgent local mental health service in your area.
If the situation is urgent but not immediately life-threatening, don't wait for the perfect provider. Reach out to one safe option today. That could be a crisis resource, a physician, a trusted peer support contact, or a counsellor with availability. When your system is overloaded, the best next step is usually the simplest one. Safety comes first. Fine-tuning the long-term plan can happen after you have support in place.
If you're looking for a private, practical next step, Interactive Counselling offers information about counselling support in Canada, including secure virtual options that can fit shift work, distance, and privacy concerns common in Northern Alberta.
Clinically Reviewed By
Amy Mosset, MCP, RCC-S
Amy Mosset is a Master Practitioner in Clinical Counselling, Clinical Supervisor, and the owner of Interactive Counselling. She provides trauma-informed, evidence-based care and clinical supervision to registered therapists, with a focus on ethical practice, client safety, and high-quality therapeutic outcomes.