

You can carry a scene for hours and still go back to shift like nothing happened. You answer the call, clean up the mess, make the report, crack a few jokes, and drive home with your shoulders still locked tight from the last alarm tone. That kind of stress doesn't always look dramatic from the outside, but it lands in the body, the sleep, the temper, and the way you come home to the people who care about you. For more information, see our Penticton trauma counselling.
First Responder Counselling in Penticton: Trauma Support for Frontline Workers is about more than talking through a bad call. It's about giving your nervous system a place to settle, making sense of what keeps replaying, and protecting the relationships and routines that start to fray under cumulative strain. If you've been relying on grit alone, that's understandable. It's also a sign you may need support that understands frontline work as a workplace injury, not a character flaw. For more information, see our counselling in Penticton.
Why Frontline Workers Carry a Different Kind of Weight
A firefighter leaves one call, then gets sent straight into another. A paramedic finishes a shift feeling “fine,” then wakes at 3 a.m. to a body that won't unclench. An RCMP member or dispatcher can go years carrying other people's emergencies, then realise the pressure has started showing up as irritability, numbness, short sleep, or a need to shut everything out. For more information, see our trauma counselling.
That's the part many people miss. Trauma for frontline workers is often cumulative, not one big event. The mind can adapt to a single hard incident, but repeated exposure to critical calls, grief, violence, and high-alert decision-making changes how the body stays ready. Counselling becomes less about “fixing” you and more about helping your system come out of permanent readiness.
What makes this different from ordinary stress
Regular stress usually eases when the pressure drops. Operational trauma doesn't always do that. You can have days off, time with family, even exercise, and still feel keyed up, flat, or strangely detached.
A useful way to think about it is the same way you'd think about physical conditioning. You wouldn't ignore a repetitive strain injury and expect it to resolve on willpower alone. Frontline mental health needs the same kind of direct, skill-based attention, and evidence-based mental fitness habits can help support the day-to-day piece between sessions.
Practical rule: if your body is still responding like the incident is happening now, your nervous system needs care, not criticism.
Understanding the Statistics on First Responder Mental Health in Canada
Canadian data makes one thing clear, frontline mental health concerns are common, and they are not a sign of personal weakness. In a Canadian first-responder screening study, 44.5% of 5,813 respondents screened positive for symptoms consistent with at least one mental disorder, which is roughly four times the ~10% rate often cited for the general population (PMC study). That gap matters because it shows how much occupational exposure changes the baseline.

What the clinical picture usually looks like
The numbers do not point to PTSD alone. In a preventive-care program study of 429 full-time first responders, 53.3% (229 people) opted into screening, and among those screened, 43% had at least one heightened mental health risk, including PTSD at 7.9%, depression at 9.6%, anxiety at 13.5%, and problematic alcohol use at 36.7% (PMC study). Among the 56 who completed follow-up clinical appointments, 67.86% were recommended for additional services, which shows how often trauma-related concerns need more than a brief check-in.
That pattern fits what many clinicians see in practice, trauma rarely shows up alone. Sleep disruption, anxiety, mood changes, and substance use can sit beside it. The literature cited in the Canadian public safety personnel guidance also notes a 44.5% positive screen rate for symptom clusters consistent with at least one mental disorder and cites guidance estimating about 30% of first responders develop behavioural health illnesses such as depression and PTSD versus 20% in the general population. For Penticton-facing care, that means screening should look wider than one diagnosis.
Why exposure and call volume matter
A British Columbia community health source notes that mental-health injuries and disorders in first responders correlate positively with call volume, and guidance for emergency workers notes around a 10% current PTSD prevalence in first responders, with risk rising as exposure accumulates (PTSD Guidelines PDF). That helps explain why someone can manage for years and then suddenly feel overwhelmed.
Trauma treatment works better when it assumes comorbidity, not neat categories. If you only ask about one symptom, you miss the rest of the picture.
What Trauma-Informed Counselling Actually Looks Like
A lot of first responders avoid therapy because they think it means retelling every horrible detail to a stranger. Good trauma-informed counselling doesn't work that way. It starts with safety, moves at a pace you can tolerate, and keeps you in control of what gets discussed.
The first session is usually about stabilising, not digging
A solid intake focuses on what's happening now, sleep, irritability, concentration, panic, numbness, avoidance, alcohol use if it's relevant, and what still helps you function. You don't need a polished story. You need a counsellor who can hear the shape of the problem without pushing for graphic disclosure before trust is built.
That first phase often includes grounding skills, ways to downshift the body, and a shared plan for what to do if a session stirs up more than expected. The point is to create enough stability that deeper trauma work becomes possible later.
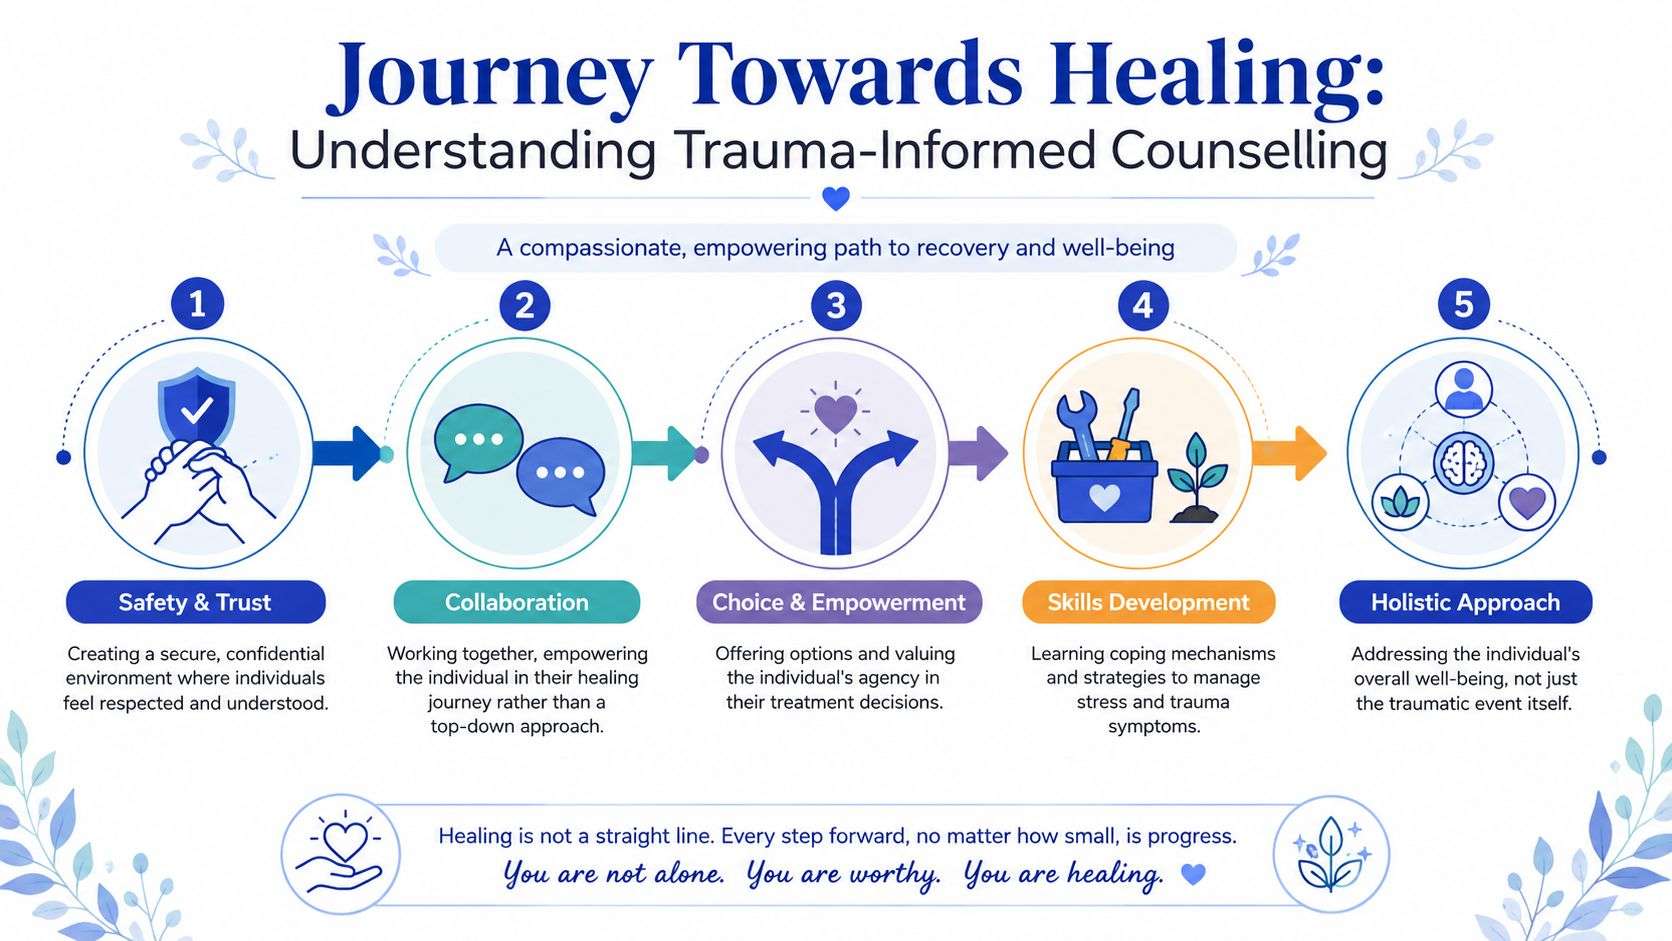
What strong trauma care includes
The method can vary, but the core is consistent.
- Safety and trust: You should know what the session is for, what the limits of confidentiality are, and what your choices are.
- Collaboration: The counsellor should ask, not assume.
- Choice and pacing: You can slow down, pause, or skip parts of the story.
- Skills between sessions: Breathing, grounding, sleep routines, and nervous system regulation matter.
- Whole-person care: Trauma, mood, relationships, substance use, and work stress often belong in the same conversation.
You do not need to “push through” therapy the way you push through a shift. The right pace is the one your system can actually hold.
How Occupational Trauma Reaches Beyond the Individual
A first responder's stress rarely stays neatly inside the person who took the call. It comes home in small ways first. A partner gets clipped responses at dinner. A child notices you're tired, distant, or easy to startle. The house feels quieter, but not calmer.
What families often notice before the worker does
Partners usually see the spillover earliest. They may notice emotional withdrawal, low patience, trouble sleeping, or a tendency to stay on duty mentally even after the uniform comes off. Families can end up managing the mood of the home around the work schedule, without knowing whether the change is temporary or part of something deeper.
That's why first responder counselling can't be reduced to individual symptom reduction. Sometimes the most useful work is relationship repair, learning how to talk about incidents without flooding the whole household, or helping a spouse make sense of the shutdown that follows repeated exposure. In some cases, couples work or family sessions are the most practical route because the stress pattern lives in the relationship, not only in the individual.
Why household support matters in Penticton
In smaller communities, people often know one another through work, school, or mutual friends. That can make disclosure feel risky, and it can make a struggling partner hesitate to ask for support of their own. A family-centred approach gives everyone a clearer path.
Research on first responders also points to an often-missed issue: spouses and partners can carry mental health strain from the responder's work, while many local service pages focus on the worker alone (PMC article). A more complete model includes the home environment, co-parenting stress, and support for the people who absorb the fallout.
Evidence-Based Treatment Approaches for Frontline Trauma
No single therapy fits every responder. What works best depends on whether the main problem is intrusive memories, panic, shutdown, shame, sleep disruption, or the sense that something in you changed after a call and never quite reset.
EMDR, CPT, and somatic work in plain language
EMDR is often used when traumatic memories feel stuck and highly charged. The counsellor guides attention in a structured way while you process the memory so it loses some of its emotional punch. It isn't about forgetting, it's about reducing the intensity that gets triggered now.
Cognitive Processing Therapy focuses on the beliefs trauma leaves behind, thoughts like “I should have done more,” “I can't trust anyone,” or “If I slow down, something bad will happen.” The work is careful and practical. You examine the story the trauma wrote in your mind and test whether it still fits.
Somatic approaches pay close attention to the body. That matters when the main symptoms live in clenching, freeze responses, breath changes, or persistent hypervigilance. The body often carries what the mind tries to organise away.
What to ask a counsellor
If you're evaluating care, ask direct questions.
- What do you use for trauma, and why that method for my situation?
- How do you handle pacing if I start to feel flooded?
- Do you work with sleep, alcohol use, or anxiety if they're part of the picture?
- Can you include my partner or family if that would help?
Using evidence based practice implementation as a lens is useful here, because good care is not a favourite technique used blindly. It's a fit between the problem, the person, and the evidence.
Accessing Counselling at Interactive Counselling in Penticton
If you're looking for a local option, Interactive Counselling offers in-person, phone, and secure virtual sessions, with daytime, evening, and weekend availability. The practice works with trauma, PTSD, anxiety, depression, grief, relationships, family concerns, and ICBC-funded counselling for people recovering from motor vehicle accidents, which can matter if a collision is part of the stress picture.
What the process usually looks like
Start with the contact step that feels easiest. Some responders prefer a phone call because it feels direct. Others send a message first because they want time to think before they talk.
You don't need to bring a perfect explanation. A short description is enough, for example, sleep has gone bad, work is staying in your head, or home life is taking the hit. From there, the counsellor can help figure out whether individual trauma work, couples support, or family-focused sessions make the most sense.
A practical note on confidentiality and funding
Many first responders worry about being judged or having their concerns talked about outside the room. Confidential, non-judgemental care matters for that reason. It lowers the barrier to showing up authentically.
If your stress is tied to a crash, there's also a concrete ICBC pathway available in Penticton. If a crash is reported to ICBC and a claim number is obtained, clients can contact an ICBC-approved counselling provider to book up to 12 pre-approved counselling sessions at no cost, and the initial sessions are fully funded if the claim is filed within 12 weeks of the accident without needing a doctor's referral (Interactive Counselling ICBC guide).
Local Crisis and Peer-Support Resources in Penticton
Therapy helps, but there are times when support needs to be immediate. If someone is in a life-threatening mental health or substance-use crisis, 9-1-1 is the right call. For urgent crisis response in Penticton, the Mobile Integrated Crisis Response Team (MICRT) pairs a uniform RCMP member with a clinical nurse specialising in mental health to respond to crisis calls, de-escalate situations, provide crisis intervention, and connect people to community services and supports (HelpStartsHere Penticton MICRT).
Where to go between sessions
For local intake, Interior Health's mental-health and substance-use service at 740 Carmi Ave is listed as the Penticton access point. The community resource guide says you can call or walk in to schedule intake, and that the site operates Monday to Friday from 8:00 a.m. to 4:00 p.m. The same guide lists a substance-use drop-in service there Monday to Friday, 1:00 p.m. to 3:00 p.m. (Penticton community resources guide).
Family and youth supports matter too
When trauma is landing at home, youth supports can be part of the plan. School District 67 lists Child & Youth Mental Health at 740 Carmi Ave for ages 0 to 18, and Foundry Penticton at 201-501 Main St for ages 12 to 24, with mental-health, substance-use, primary-care, and peer-support services (SD67 resource page). That matters because family spillover doesn't stop at the door.
The point isn't to self-diagnose. It's to have a clearer sense of what anxiety can look like when stress has been running too long.

Common Questions First Responders Ask Before Starting Therapy
Will therapy affect my job or get back to my employer?
Confidential counselling is designed to protect your privacy. The exact limits of confidentiality should be explained clearly at the start, including the rare situations where safety concerns change what must be shared. You should never have to guess.
What if I'm not sure I have PTSD?
That's common. Many first responders come in because they feel off, not because they can name a diagnosis. Sleep problems, numbness, anxiety, irritability, or family strain can all be valid reasons to start.
How do I find someone who understands frontline culture?
Look for trauma-informed care, not just general counselling. A good fit is a counsellor who can talk about exposure, cumulative stress, shift work, and family impact without making you educate them from scratch.
Is couples or family counselling appropriate?
Yes, when the work stress is affecting home life. If your partner is walking on eggshells or your kids are reacting to the tension, bringing them into care can help stabilise the whole system.
What if I'm worried therapy will make things worse before they get better?
That fear makes sense. Good trauma counselling should be paced, collaborative, and grounded in skills so you don't get overwhelmed. If a therapist pushes too hard too soon, that's a signal to slow down or reassess the fit.
If you're carrying trauma from frontline work and you're ready for support that respects both the job and the home it comes back to, Interactive Counselling offers trauma-informed care for individuals, couples, and families in Penticton. Reaching out can be the first practical step toward steadier sleep, clearer thinking, and a home life that feels less shaped by the last call.
Clinically Reviewed By
Amy Mosset, MCP, RCC-S
Amy Mosset is a Master Practitioner in Clinical Counselling, Clinical Supervisor, and the owner of Interactive Counselling. She provides trauma-informed, evidence-based care and clinical supervision to registered therapists, with a focus on ethical practice, client safety, and high-quality therapeutic outcomes.


